


- IPC GENERAL
- Comorbidities, IPC Publications, Research, Treatment, Treatment Guidelines
A cancer diagnosis changes everything for a patient. It should not, however, automatically eliminate their access to effective psoriasis care. A new IPC manuscript published in the JAAD Reviews addresses a gap that clinicians on both sides of the oncology-dermatology divide have long navigated without formal guidance: how to make individualized, evidence-based decisions about systemic psoriasis therapy when a patient has cancer.
A Gap That Has Real Consequences
Psoriasis and cancer share more common ground than clinicians may expect. Patients with psoriasis face elevated risks of certain malignancies, including lymphoma and non-melanoma skin cancer, and the systemic inflammation that drives psoriasis may complicate oncologic management in both directions. Despite this, systemic psoriasis therapy is frequently discontinued or never initiated in oncology settings, often based on broad precaution rather than specific evidence.
One of the most consistent findings the authors document is that psoriasis severity is underestimated in oncology settings. Dermatologists and oncologists are not always working from the same framework when it comes to what constitutes moderate to severe disease. That gap can lead to undertreated skin disease in patients who already carry a significant burden.
Paolo Gisondi, MD, lead author of the manuscript, puts it directly. “Too often, systemic psoriasis therapy is discontinued or never initiated in patients with cancer, even when the evidence supports safe and effective options. This guidance is a step toward closing that gap and ensuring that patients with cancer receive the psoriasis care they deserve.”
What the Evidence Actually Supports
The manuscript walks through the available evidence for systemic therapy classes in the context of active or prior malignancy, and the findings are more nuanced than a blanket contraindication.
IL-17 inhibitors and IL-23 inhibitors emerge as appropriate first-line options for most patients with cancer who require systemic psoriasis therapy. Their mechanisms target specific inflammatory pathways rather than broadly suppressing immune function, and the available data do not support elevated oncologic risk with their use. Where first-line agents are unavailable, phototherapy, acitretin, methotrexate, dimethyl fumarate, and apremilast remain reasonable if less effective choices, while TNF inhibitors, IL-12/IL-23p40 inhibitors, and deucravacitinib warrant caution. Cyclosporine, by contrast, is not recommended: its broad immunosuppressive profile and established association with non-melanoma skin cancer make it a poor fit in this population.
Therapeutic Options in Patients with Psoriasis and Active or Prior Cancer
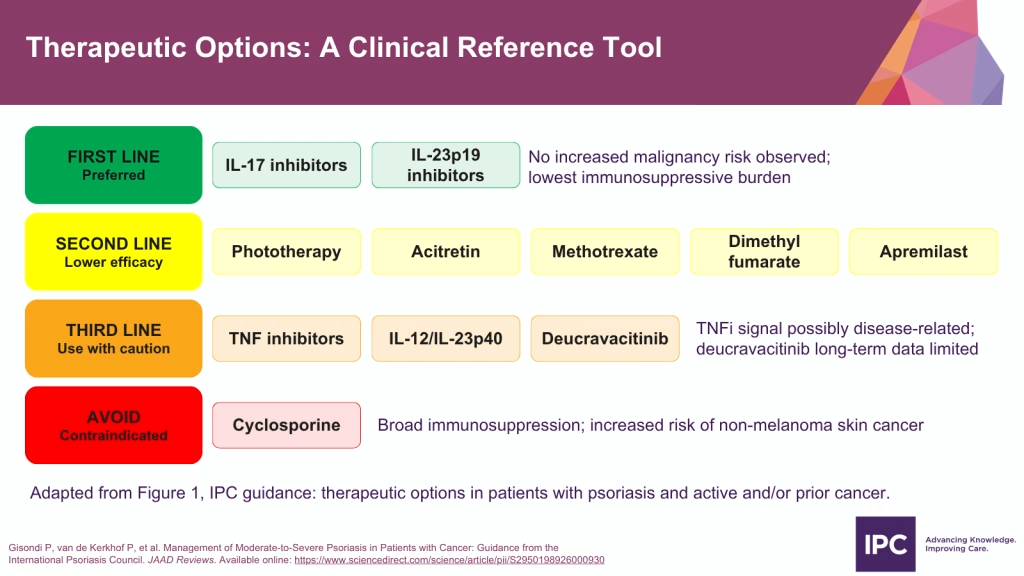
Icotrokinra, an oral IL-23inhibitor, is discussed in the manuscript as a potential first-line option based on its mechanism of action. It is not included in the table above because direct clinical evidence in this population remains limited.
The authors also make clear that severity assessment must anchor every treatment decision. Using IPC’s established severity criteria in oncology settings, where the tendency to deprioritize skin disease is common, is one of the paper’s central practical recommendations. A patient who meets IPC’s criteria for systemic therapy should be recognized as a candidate for treatment, regardless of what else is on their problem list.
Collaboration as a Clinical Imperative
No single clinician owns the full picture for a patient managing both psoriasis and cancer. The manuscript frames dermatologist-oncologist collaboration not as a best practice but as a requirement for good care. Treatment decisions need to account for the patient’s current oncologic status, the type and stage of malignancy, the therapies being used to treat the cancer, and the trajectory of both conditions over time.
The therapeutic options figure (Figure 1) in the paper is designed to support exactly this kind of shared decision-making, providing a visual reference that can travel across specialty lines.
IPC Chief Medical Officer Peter van de Kerkhof, MD, PhD, reflects on what this means for clinical practice. “Psoriasis management does not pause when a patient receives a cancer diagnosis. This publication gives dermatologists and oncologists a shared framework for making informed, individualized treatment decisions that keep psoriasis severity at the center of the conversation.”
Putting the Guidance Into Practice
For clinicians treating psoriasis patients with a history of cancer or an active malignancy, the manuscript offers a starting point grounded in evidence rather than institutional habit. It points clinicians toward the therapy classes best supported for this population, reinforces that psoriasis severity deserves the same weight in an oncology setting as anywhere else, and frames the oncologist not as a gatekeeper to work around but as a partner in the decision. The therapeutic options figure in the manuscript are designed to span specialties, providing both sides with a common reference point when a treatment plan needs to change.
Read the full manuscript in JAAD Reviews
IPC has also developed a summary slide deck covering the key therapeutic options and severity criteria discussed in the paper. Download the slides to reference during patient visits or share with colleagues:





